
Full text
Source and licence. Originally published by Scientific & Academic Publishing in American Journal of Medicine and Medical Sciences, Vol. 14 No. 8 (2024), pp. 2004-2008, DOI 10.5923/j.ajmms.20241408.13. Republished under the Creative Commons Attribution 4.0 International licence (CC BY 4.0). View the original article.
1. Introduction
The majority of patients undergoing surgical treatment for flatfoot suffer from rigid flatfoot. Most of them have tarsal coalition and shortened Achilles tendon.
2. Principles of Surgical Treatment
The main principle of surgical treatment for flatfoot in children is stabilization, as the main biomechanical issue of flatfoot is instability.
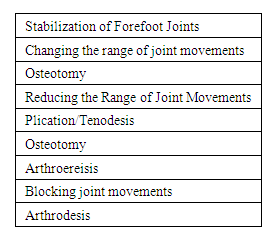 |
Figure 1. Principles of Forefoot Stabilization |
Methods that alter the range of joint motion include various options for calcaneal tuberosity osteotomy (sliding calcaneal tuberosity osteotomy (Koutsogiannis), closed-wedge calcaneal tuberosity osteotomy (Dwyer)), as well as various options for supramalleolar osteotomy. These methods do not change the amplitude of joint movement in the forefoot but alter their position [2]. Surgical methods in this group are rarely used alone. Among all the listed methods, the sliding calcaneal tuberosity osteotomy is most commonly used as an adjunct to other correction methods.
The most common methods for treating flatfoot are those that reduce the range of joint motion. These methods include surgical interventions on the soft tissue structures of the medial edge of the foot (plicature and augmentation of the posterior tibial tendon, interventions on the medial and plantar structures such as the deltoid and calcaneonavicular ligaments). Due to the high rate of recurrences, these methods are rarely used alone. Furthermore, considering that posterior tibial tendon dysfunction is almost nonexistent in children, the use of these methods in children is significantly limited. The most widely used methods for correcting flatfoot in children are subtalar arthroereisis and calcaneal lengthening osteotomy (Ford S. E., Scannell B. P., 2017).
In cases of pronounced degenerative changes in the joints of the forefoot and the impossibility of restoring movements, methods that block joint movements are used, such as various arthrodesis options. These may include local arthrodeses (subtalar joint, calcaneonavicular joint, naviculocuneiform joint, and others). Due to severe biomechanical disturbances in the forefoot and the development of degenerative changes in adjacent joints, the use of these methods in children is limited [3].
Subtalar Arthroereisis.
Ø Indications for the method: Flatfoot with shortening of the Achilles tendon, tarsal coalitions, conditions suitable for the method.
Ø Conditions for implementation: Normal mobility of the subtalar joint.
Ø Degree of correction: Subtalar and Chopart joints.
Ø Optimal age for the method: 9-12 years.
Ø Immobilization after the method: Depending on the type of Achilles tendon lengthening, 2-4 weeks.
The biomechanical essence of this method is to limit the mobility of the subtalar joint and block excessive eversion of the foot. There are many variants of subtalar arthroereisis. Most subtalar implants are placed in the tarsal sinus. Since proprioceptive and nociceptive nodes are located in this area, pain syndrome often occurs in the tarsal sinus area after subtalar implant placement. According to the literature, the incidence of pain after using subtalar implants can reach 46% (Needleman R. L., 2006). Most publications covering the use of various implants are limited to small series of observations, i.e., 30-50 patients [6,7]. Among all the subtalar arthroereisis options, the method using a blocking screw (“calcaneo-stop”) is characterized by numerous studies on a large clinical material (M.DePellegrin, 2014). Given the features of the metal structure placement (the screw is placed in the calcaneus), the frequency of pain syndromes is significantly lower, since the screw is located in the entry part of the tarsal sinus.
The application of such a variant of arthroereisis is considered a minimally invasive method, with the size of the skin incision determined only by the diameter of the screw head. The correction in both arthroereisis variants is comparable in degree; however, the use of a blocking screw inserted into the talus allows for adjustment of the correction degree by changing the insertion depth of the screw. The optimal age for this subtalar arthroereisis variant is 9-12 years. This method allows for the removal of metal structures 2-3 years after installation [8].
After subtalar arthroereisis, changes in gait (reduction of foot progression angle during walking) and elevation of the first metatarsal bone often occur (Figure 2). Over time, these changes decrease and usually do not bother patients (M. DePellegrin, 2014).
Calcaneal Lengthening Osteotomy (Evans Method).
Ø Condition for implementation: Normal mobility of the Chopart joint.
Ø Indications for the method: Flatfoot with shortening of the Achilles tendon, tarsal coalitions, conditions suitable for the method.
Ø Degree of correction: Mainly the Chopart joint.
Ø Optimal age for the method: 12-14 years.
Ø Immobilization after the method: Removal of pins, change of cast, suture removal after 6 weeks, overall immobilization duration after the method – 2.5-3 months, depending on consolidation speed [4,5].
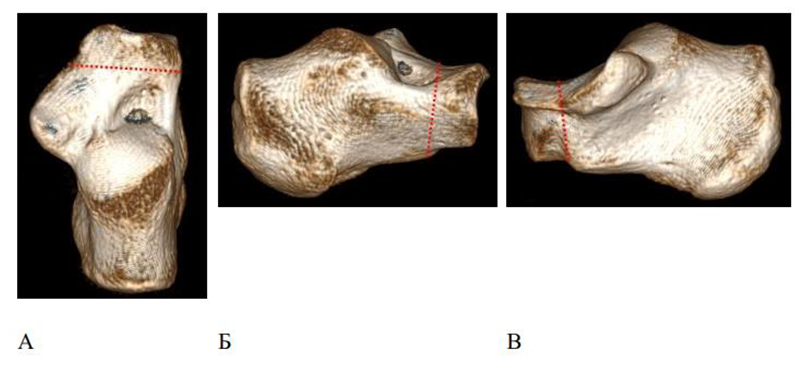 |
Figure 2. Flatfoot with calcaneal osteotomy by Evans method. (Mosca V.S., The Journal of Foot and Ankle Surgery – 2017, 56(5)) |
Given the features of calcaneal bone density in young children, calcaneal lengthening osteotomy is performed at an older age (after 12 years). The method enhances the extension of the lateral column of the hindfoot through calcaneal osteotomy. The artificial fracture line is located between the middle and anterior articular facets, 1.5 cm proximal to the calcaneocuboid joint. Bone fragments are separated, and a 1 cm autograft is placed between them. If necessary, the tendons of the peroneal muscle group are lengthened. Thus, the lateral column of the foot is lengthened, and eversion correction is achieved.
The optimal area for osteotomy is between the medial and anterior facets of the subtalar joint [20] (Mosca V.S., 1995) (Figure 1).
Flatfoot with calcaneal osteotomy is not only associated with the location between the medial and anterior facets of the subtalar joint but may also be associated with anterior tilt. To determine the area for calcaneal osteotomy, intraoperative anteroposterior radiography of the calcaneus with visualization of the sustentaculum tali during plantar flexion of the foot can be used, and the osteotomy is performed directly anterior to the sustentaculum tali.
When performing anteroposterior radiography during foot flexion, the anterior edge of the sustentaculum tali is well visible, and using a navigation needle inserted into the calcaneus, osteotomy can be performed between the medial and anterior facets of the subtalar joint [9,10].
In cases where pronounced valgus of the hindfoot remains, the Evans method can be supplemented with medializing calcaneal osteotomy by Koutsogiannis (Koutsogiannis E., 1971).
In cases of elevation of the first metatarsal bone, the Evans method is supplemented by flexion osteotomy of the first cuneiform bone by Cotton method (Boffeli T. J., Schnell K. R., 2017).
The primary group of patients with flatfoot undergoing surgical treatment consists of those with an elongated triceps surae muscle. There are various methods for elongating the triceps surae muscle, depending on the extent and location of the elongation. Most patients with flatfoot experience isolated elongation of the gastrocnemius muscle. For gastrocnemius elongation, the Vulpius method is used, in which the skin and subcutaneous fat are cut posteriorly by 2.0-2.5 cm, and the aponeurosis is incised in a Z-shape followed by an aponeurotomy. Alternatively, the Silfverskiold and Barouk method involves dissecting the heads of the gastrocnemius muscles proximally by 3.0-3.5 cm, or isolating the medial head of the gastrocnemius muscle (Barouk L. S., 2014). For Achilles tendon elongation, the Hoke method is employed, wherein a percutaneous Achilles tenoplasty is performed with semicircular incisions medially and laterally (Volpon J. B., Natale L. L., 2019). Figure 2 illustrates the options for triceps surae muscle elongation.
Though there are more techniques for triceps surae elongation, the figure shows the most commonly used methods in practice. The immobilization period varies depending on the method. For example, immobilization with a cast lasts for 4 weeks after Hoke Achilles tenoplasty and Vulpius aponeurotomy, whereas it lasts for 1.5 weeks after the Barouk medial head gastrocnemius resection. In some cases, immobilization can be avoided during stretching with the Barouk method. Notably, Achilles tenoplasty offers the greatest potential for correction, whereas the Barouk method increases foot dorsiflexion by 10-15 degrees.
Surgical Treatment of Children with Tarsal Coalition; There are two main approaches to the surgical treatment of children with tarsal coalition: direct intervention on the coalition and correction of the accompanying foot deformity. The method for correcting foot deformity depends on the type of intervention on the coalition. Tarsal coalition interventions are divided into resection and arthrodesis methods. Arthrodesis methods are rarely used and only in cases of severe degenerative changes in the forefoot. The severity of such changes is assessed based on X-rays (degree of osteoarthritis of the talonavicular joint) and MRI and CT scans (subtalar joint). It should be noted that the degree of osteoarthritis of the talonavicular joint does not always depend on the size of bone growths, as the “beak” syndrome in tarsal coalitions can create the impression of pronounced osteoarthritis, although this symptom does not play a role in the direct manifestation of degenerative changes (Crim, J., 2008).
The assessment of the severity of degenerative changes is also conducted through intraoperative determination of forefoot mobility after resection (Cass, A. D., Camasta, C. A., 2010). During resection of the talocalcaneal coalition, the condition of the joint surfaces of the posterior facet of the subtalar joint can be evaluated.
Currently, positive results are achieved through transposition of the long peroneal muscle tendon and shortening of the posterior tibial muscle tendon combined with arthrodesis of the navicular and cuneiform bones.
3. Conclusions
Flatfoot is one of the most common conditions in pediatric orthopedics (Konyukhov, Lapkin, 2000, 2003). The primary condition for diagnosing and assessing flatfoot in children is the initial differentiation between pathological and physiological forms of flatfoot. Conservative treatment of rigid flatfoot in children is practically ineffective and can only temporarily reduce pain and discomfort. The rigid form of static flatfoot in children occurs in 18-20% of cases of overall musculoskeletal pathology. Currently, there are no objective diagnostic methods and treatment algorithms for rigid flatfoot depending on severity, tarsal bone deformation, foot mobility, and posterior tibial tendon dysfunction (PTTD). The primary treatment method for rigid flatfoot in children is surgical intervention. The most commonly used surgical methods for correcting foot deformity are subtalar arthroereisis and calcaneal lengthening osteotomy. The use of the subtalar arthroereisis method to correct tarsal bone deformity, foot mobility, and severe stages of posterior tibial tendon dysfunction has proven ineffective. When treating rigid flatfoot in children, it is necessary to consider the severity of the deformity, the degree of navicular bone fusion, the mobility index, and the stage of posterior tibial tendon dysfunction.